
The Anatomical Relationship Between the Transverse-Sigmoid Complex and Skull Landmarks in a 3D CTV Imaging Study
คำสำคัญ:
Transverse-sigmoid complex, Asterion, Digastric point, Volume-rendering 3D imaging, Retrosigmoid craniotomy, Skull bony landmarksบทคัดย่อ
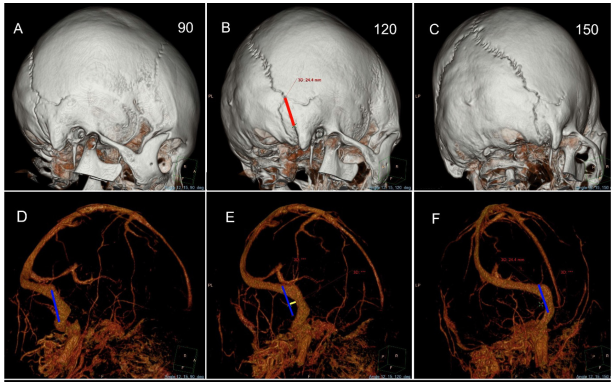
Background: The retrosigmoid craniotomy is one of the most common approaches in neurosurgery. The bony landmarks related to the transverse-sigmoid sinus are important for performing surgery safely and effectively. This study investigated the relationship between the transverse-sigmoid sinus complex and external skull landmarks, focusing on the asterion–digastric point line as a reference for the vertical sigmoid sinus and related anatomy. Method: Radiographic study was conducted using 51 three-dimensional computed tomography venography scans obtained from patients older than 15 years at Ramathibodi Hospital between 2021 and 2023. Volume-rendering techniques were applied to identify the asterion, the digastric point, the transverse-sigmoid sinus junction, and the vertical segment of the sigmoid sinus. Measurements were taken at the proximal, mid, and distal portions relative to the asterion-digastric point line, with the angles in the x (coronal), y (sagittal), and z (rotational) axes set at 12°, 15°, and 120°, respectively. Results: The line connecting the asterion and the digastric point serves as the most reliable landmark (100%) for locating the vertical segment of the sigmoid sinus on both sides. The mean distances from this line to the medial border of the vertical part of the sigmoid sinus were 4.16±2.45 mm, 7.90±2.33 mm, and 3.24±1.64 mm from proximal to distal, respectively. The mastoid emissary foramen is more commonly found on the right side than on the left and is mostly located medial to this line. The occipitomastoid suture was found to be medial to the asterion- digastric point line in all cases. The mean distance from the digastric point to the occipitomastoid suture is 9.36 ± 1.30 mm on the right side and 9.48 ± 1.22 mm on the left side. Additionally, the right sigmoid sinus was significantly larger (7.50 ± 1.22 mm, P < 0.001) than the left in most cases. Conclusion: Recognizing the asterion-digastric point line and the occipitomastoid suture as the most reliable landmark for the vertical part of sigmoid sinus helps surgeons avoid inadvertent injury to the transversesigmoid venous sinus during routine craniotomy in this area.
Downloads
เอกสารอ้างอิง
References
Leuze C, Neves CA, Gomez AM, Navab N, Blevins N, Vaisbuch Y, et al. Augmented reality for retrosigmoid craniotomy planning. J Neurol Surg B Skull Base. 2022;83(Suppl 2):e564-e573. https://doi.org/10.1055/s-0041-1735509.
Teranishi Y, Kohno M, Sora S, Sato H. Determination of the keyhole position in a lateral suboccipital retrosigmoid approach. Neurol Med Chir (Tokyo). 2014;54(4):261-6. https://doi.org/10.2176/nmc.oa2013-0020.
Rhoton AL Jr. The cerebellopontine angle and posterior fossa cranial nerves by the retrosigmoid approach. Neurosurgery. 2000;47(3 Suppl):S93-129. https://doi.org/10.1097/00006123-200009001-00013.
Yamashima T, Lee JH, Tobias S, Kim CH, Chang JH, Kwon JT. Surgical procedure “simplified retrosigmoid approach” for C-P angle lesions. J Clin Neurosci. 2004;11(2):168-71. https://doi.org/10.1016/j.jocn.2003.06.004.
Raso JL, Silva Gusmão SN. A new landmark for finding the sigmoid sinus in suboccipital craniotomies. Neurosurgery. 2011;68(1 Suppl Operative):ons1-6; discussion ons6. https://doi.org/10.1227/NEU.0b013e3182082afc.
Day JD, Kellogg JX, Tschabitscher M, Fukushima T. Surface and superficial surgical anatomy of the posterolateral cranial base: significance for surgical planning and approach. Neurosurgery. 1996;38(6):1079-83; discussion 1083-4. https://doi.org/10.1097/00006123-199606000-00003.
Tubbs RS, Loukas M, Shoja MM, Bellew MP, Cohen-Gadol AA. Surface landmarks for the junction between the transverse and sigmoid sinuses: application of the “strategic” burr hole for suboccipital craniotomy. Neurosurgery. 2009;65(6 Suppl):37-41; discussion 41. https://doi.org/10.1227/01.NEU.0000341517.65174.63.
Kizilkanat E, Boyan N, Ozsahin E, Soames R, Oguz O. Surface landmarks for suboccipital craniotomy. Neurosurg Q. 2013;23(2):133-6. https://doi.org/10.1097/WNQ.0b013e318266c42d.
Avci E, Kocaogullar Y, Fossett D, Caputy A. Lateral posterior fossa venous sinus relationships to surface landmarks. Surg Neurol. 2003;59(5):392-7; discussion 397. https://doi.org/10.1016/S0090-3019(03)00037-5.
Kim YS, Jung SH, Lim DH, Kim TS, Kim JH, Lee JK. Traumatic dural venous sinus injury. Korean J Neurotrauma. 2015;11(2):118-23. https://doi.org/10.13004/kjnt.2015.11.2.118.
Hu W, Zhou J, Liu ZM, Li Y, Cai QF, Hu XM, et al. Computed tomography study of the retrosigmoid craniotomy keyhole approach using surface landmarks. Int J Clin Pract. 2023;2023:5407912. https://doi.org/10.1155/2023/5407912.
Gharabaghi A, Rosahl SK, Feigl GC, Samii A, Liebig T, Heckl S, et al. Surgical planning for retrosigmoid craniotomies improved by 3D computed tomography venography. Eur J Surg Oncol. 2008;34(2):227-31. https://doi.org/10.1016/j.ejso.2007.01.032.
Hampl M, Kachlik D, Kikalova K, Riemer R, Halaj M, Novak V, et al. Mastoid foramen, mastoid emissary vein and clinical implications in neurosurgery. Acta Neurochir (Wien). 2018;160(7):1473-82. https://doi.org/10.1007/s00701-018-3564-2.
Zhou W, Di G, Rong J, Hu Z, Tan M, Duan K, et al. Clinical applications of the mastoid emissary vein. Surg Radiol Anat. 2023;45(1):55-63. https://doi.org/10.1007/s00276-022-03060-0.
Mwachaka PM, Hassanali J, Odula PO. Anatomic position of the asterion in Kenyans for posterolateral surgical approaches to cranial cavity. Clin Anat. 2010;23(1):30-3. https://doi.org/10.1002/ca.20888.
Jurgaitis J, Jukna Š, Terbetas G. Anatomical landmarks for transverse-sigmoid sinus junction: a cadaveric study. Cureus. 2024;16(4):e59278. https://doi.org/10.7759/cureus.59278.
Li R, Qi L, Yu X, Li K, Bao G. Mastoid notch as a landmark for localization of the transverse-sigmoid sinus junction. BMC Neurol. 2020;20(1):111. https://doi.org/10.1186/s12883-020-01688-2.
Matsuo S, Komune N, Kurogi R, Akagi Y, Iihara K. Relationship between the horizontal part of the sigmoid sinus and the line through the digastric point and posterior edge of the condyle: an anatomic and radiologic study. World Neurosurg. 2018;114:e597-e604. https://doi.org/10.1016/j.wneu.2018.03.038.
Gilkes A, Rajaram-Gilkes M, Cardona JJ, Reina F, Carrera A, Iwanaga J, et al. The occipitalis muscle as an adjunct superficial landmark for the transverse sinus and transverse-sigmoid junction: an anatomical study with application to posterior cranial fossa surgery. Cureus. 2023;15(5):e39723. https://doi.org/10.7759/cureus.39723.
Broekx S, Stevesyns DT, Menovsky T. The auricula as a new surgical landmark for the transverse-sigmoid-sinus-transition. Brain Spine. 2024;4:102757. https://doi.org/10.1016/j.bas.2024.102757.
Jian ZH, Sheng MF, Li JY, Li Y, Weng ZJ, Chen G. Precise localization in craniotomy with a retrosigmoid keyhole approach: microsurgical anatomy and clinical study. Front Surg. 2022;9:809098. https://doi.org/10.3389/fsurg.2022.809098.
Isikay I, Cekic E, Baylarov B, Tunc O, Hanalioglu S. Narrative review of patient-specific 3D visualization and reality technologies in skull base neurosurgery: enhancements in surgical training, planning, and navigation. Front Surg. 2024;11:1427844. https://doi.org/10.3389/fsurg.2024.1427844.
Jha DK, Khera P, Bhaskar S, Garg M. Three-dimensional volume rendering: an underutilized tool in neurosurgery. World Neurosurg. 2019;130:485-92. https://doi.org/10.1016/j.wneu.2019.07.065.
Zhou B, Li MH, Wang W, Xu HW, Cheng YD, Wang J. Three-dimensional volume-rendering technique in the angiographic follow-up of intracranial aneurysms embolized with coils. J Neurosurg. 2010;112(3):674-80. https://doi.org/10.3171/2009.7.JNS081718.
Kubo M, Mizutani T, Shimizu K, Matsumoto M, Iizuka K. New methods for determination of the keyhole position in the lateral suboccipital approach to avoid transverse-sigmoid sinus injury: proposition of the groove line as a new surgical landmark. Neurochirurgie. 2021;67(4):325-9. https://doi.org/10.1016/j.neuchi.2020.12.009.
ดาวน์โหลด
เผยแพร่แล้ว
รูปแบบการอ้างอิง
ฉบับ
ประเภทบทความ
สัญญาอนุญาต
ลิขสิทธิ์ (c) 2026 วารสารประสาทศัลยศาสตร์ไทย

อนุญาตภายใต้เงื่อนไข Creative Commons Attribution-NonCommercial-NoDerivatives 4.0 International License.
##default.contextSettings.thaijo.licenseTerms##

