
Acute treatment response among patients with migraine subtypes: A real-world study in Thailand
Keywords:
Acute treatment, aura subtypes, migraine disorders, migraine with aura, migraine with complex aura, treatment responseAbstract
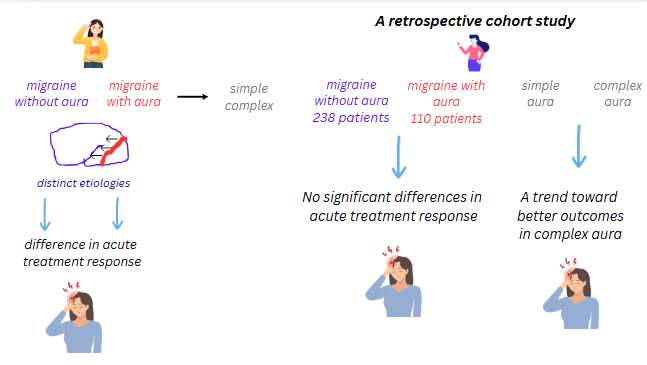
Background: Migraines with and without aura may have distinct etiologies. Aura can vary in complexity (from simple to complex), which potentially reflects differences in cortical involvement and influences acute treatment response.
Objective: To compare the acute treatment responses between patients with migraine with and without aura, as well as aura complexity levels, in Thailand.
Methods: A retrospective cohort study was conducted from January 3, 2007, to June 30, 2022, at the Chulalongkorn Comprehensive Headache Center, King Chulalongkorn Memorial Hospital, Thai Red Cross Society. Baseline data were retrieved from the baseline case-record forms, while clinical data were obtained from paper headache diaries and follow-up case-record forms. The primary outcome was a 2 h pain-free response; secondary outcomes included pain scores and associated symptoms.
Results: Among the 358 patients (110 with aura, 248 without), baseline characteristics were largely similar, except for differences in the associated symptoms (photophobia and phonophobia) and the use of antiepileptic drugs for migraine prevention. No significant differences in acute treatment response were found between the groups. However, patients with complex auras exhibited a trend toward better outcomes, with higher 2 h pain-free rates (44.5% vs. 23.9%) and greater improvement in pain duration (33.3% vs. 22.8%) compared with patients with simple auras.
Conclusion: Acute treatment responses did not differ significantly across migraine types, although patients with complex aura may respond better.
Downloads
References
Qubty W, Patniyot I. Migraine pathophysiology. Pediatr Neurol 2020;107:1-6.
https://doi.org/10.1016/j.pediatrneurol.2019.12.014
Dodick DW. A Phase-by-Phase review of migraine pathophysiology. Headache 2018;58 Suppl 1:4-16.
https://doi.org/10.1111/head.13300
Sanchez Del Rio M, Cutrer FM. Pathophysiology of migraine aura. Handb Clin Neurol 2023;198:71-83.
https://doi.org/10.1016/B978-0-12-823356-6.00016-0
Chayasirisobhon S. Somatosensory evoked potentials in acute migraine with sensory aura. Clin Electroencephalogr 1995;26:65-9.
https://doi.org/10.1177/155005949502600109
DeLange JM, Cutrer FM. Our evolving understanding of migraine with aura. Curr Pain Headache Rep 2014;18:453.
https://doi.org/10.1007/s11916-014-0453-0
Headache Classification Committee of the International Headache Society (IHS) The International Classification of Headache Disorders, 3rd edition. Cephalalgia 2018;38:1-211.
https://doi.org/10.1177/0333102417738202
Petrusic I, Viana M, Dakovic M, Goadsby P, Zidverc-Trajkovic J. Proposal for a migraine aura complexity score. Cephalalgia 2019;39:732-741.
https://doi.org/10.1177/0333102418815487
Petrusic I, Viana M, Dakovic M, Zidverc-Trajkovic J. Application of the Migraine Aura Complexity Score (MACS): Clinical and Neuroimaging Study. Front Neurol 2019;10:1112.
https://doi.org/10.3389/fneur.2019.01112
Lin QF, Xia QQ, Zeng YL, Wu XY, Ye LF, Yao LT, et al. Prevalence of migraine in Han Chinese of Fujian province: An epidemiological study. Medicine (Baltimore) 2018;97:e13500.
https://doi.org/10.1097/MD.0000000000013500
Evers S, Tassorelli C. Migraine with aura. Handb Clin Neurol 2023;198:169-186.
https://doi.org/10.1016/B978-0-12-823356-6.00009-3
Russell MB, Rasmussen BK, Fenger K, Olesen J. Migraine without aura and migraine with aura are distinct clinical entities: a study of four hundred and eighty-four male and female migraineurs from the general population. Cephalalgia 1996;16:239-45.
https://doi.org/10.1046/j.1468-2982.1996.1604239.x
Hansen JM, Goadsby PJ, Charles A. Reduced efficacy of sumatriptan in migraine with aura vs without aura. Neurology. 2015;84:1880-5.
https://doi.org/10.1212/WNL.0000000000001535
Johnson HF, Goadsby PJ, Gelfand AA. Predictors of triptan response in pediatric migraine. Pediatr Neurol 2016;58:37-40.
https://doi.org/10.1016/j.pediatrneurol.2016.01.022
Banerjee M, Findley LJ. Sumatriptan in the treatment of acute migraine with aura. Cephalalgia 1992;12:39-44.
https://doi.org/10.1046/j.1468-2982.1992.1201039.x
Subcutaneous Sumatriptan International Study Group. Treatment of migraine attacks with sumatriptan. N Engl J Med 1991;325:316-21.
https://doi.org/10.1056/NEJM199108013250504
Derry CJ, Derry S, Moore RA. Sumatriptan (subcutaneous route of administration) for acute migraine attacks in adults. Cochrane Database Syst Rev 2012;2012:CD009665.
https://doi.org/10.1002/14651858.CD009665
Derry CJ, Derry S, Moore RA. Sumatriptan (oral route of administration) for acute migraine attacks in adults. Cochrane Database Syst Rev 2012;2012:CD008615.
https://doi.org/10.1002/14651858.CD008615.pub2
Derry CJ, Derry S, Moore RA. Sumatriptan (intranasal route of administration) for acute migraine attacks in adults. Cochrane Database Syst Rev 2012;2012:CD009663.
https://doi.org/10.1002/14651858.CD009663
Hansen JM, Charles A. Differences in treatment response between migraine with aura and migraine without aura: lessons from clinical practice and RCTs. J Headache Pain 2019;20:96.
https://doi.org/10.1186/s10194-019-1046-4
Takeshima T, Komori M, Tanji Y, Ozeki A, Tatsuoka Y. Efficacy of lasmiditan across patient and migraine characteristics in Japanese patients with migraine: a secondary analysis of the MONONOFU trial. Adv Ther 2022;39:5274-5288.
https://doi.org/10.1007/s12325-022-02304-0
Chiang CC, Arca KN, Dunn RB, Girardo ME, Quillen JK, Dodick DW, et al. Real-world efficacy, tolerability, and safety of ubrogepant. Headache 2021;61:620-627
https://doi.org/10.1111/head.14062
von Elm E, Altman DG, Egger M, Pocock SJ, Gøtzsche PC, Vandenbroucke JP. The Strengthening the Reporting of Observational Studies in Epidemiology (STROBE) statement: guidelines for reporting observational studies. PLoS Med 2007;4:e296.
https://doi.org/10.1371/journal.pmed.0040296
Benchimol EI, Smeeth L, Guttmann A, Harron K, Moher D, Petersen I, et al. The REporting of studies Conducted using Observational Routinely-collected health Data (RECORD) statement. PLoS Med 2015;12:e1001885.
https://doi.org/10.1371/journal.pmed.1001885
Headache Classification Subcommittee of the International Headache Society. The International Classification of Headache Disorders: 2nd edition. Cephalalgia 2004;24 Suppl 1:9-160.
Headache Classification Committee of the International Headache Society (IHS). The International Classification of Headache Disorders, 3rd edition (beta version). Cephalalgia 2013;33:629-808.
https://doi.org/10.1177/0333102413485658
Asawavichienjinda T, Storer RJ. Preventive treatment response associated with migraine aura subtypes in a Thai population. Front Hum Neurosci 2023;16:1065859.
https://doi.org/10.3389/fnhum.2022.1065859
Ha H, Gonzalez A. Migraine headache prophylaxis. Am Fam Physician 2019;99:17-24.
Bigal ME, Bordini CA, Tepper SJ, Speciali JG. Intravenous magnesium sulphate in the acute treatment of migraine without aura and migraine with aura. A randomized, double-blind, placebo-controlled study. Cephalalgia 2002;22:345-53.
https://doi.org/10.1046/j.1468-2982.2002.00364.x
Bigal ME, Bordini CA, Tepper SJ, Speciali JG. Intravenous dipyrone in the acute treatment of migraine without aura and migraine with aura: a randomized, double blind, placebo controlled study. Headache 2002;42:862-71.
https://doi.org/10.1046/j.1526-4610.2002.02204.x
Cete Y, Dora B, Ertan C, Ozdemir C, Oktay C. A randomized prospective placebo-controlled study of intravenous magnesium sulphate vs. metoclopramide in the management of acute migraine attacks in the Emergency Department. Cephalalgia 2005;25:199-204.
https://doi.org/10.1111/j.1468-2982.2004.00840.x
Lai J, Dilli E. Migraine aura: updates in pathophysiology and management. Curr Neurol Neurosci Rep 2020;20:17.
Downloads
Published
How to Cite
Issue
Section
License
Copyright (c) 2026 Chulalongkorn Medical Journal

This work is licensed under a Creative Commons Attribution-NonCommercial-NoDerivatives 4.0 International License.








